
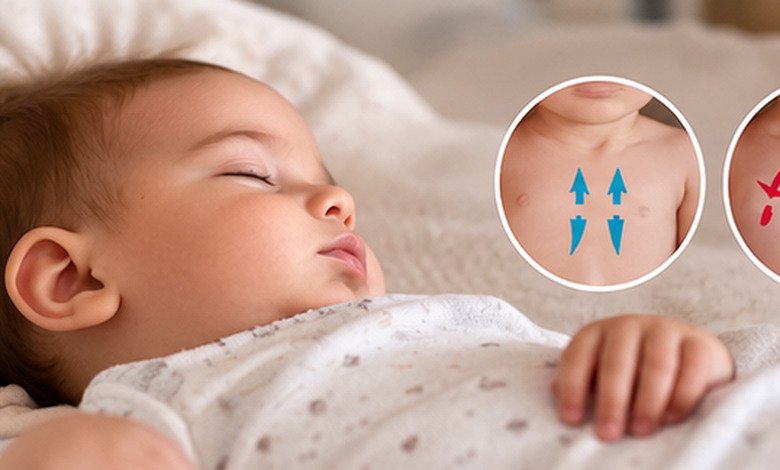
Normal baby breathing vs retractions explained clearly, including warning signs that need prompt medical attention.
Normal baby breathing can be fast, irregular, and occasionally interrupted by brief pauses, especially in newborns. Retractions are different: they occur when the skin and soft tissues around the ribs, breastbone, or neck visibly pull inward during breathing, indicating increased work of breathing.
Watching a newborn breathe can be surprisingly unsettling. One minute the baby seems peaceful; the next, the breathing speeds up, the belly rises and falls, or there is a tiny pause that makes a parent wonder, “Is that normal?”
The good news is that newborn breathing genuinely looks different from adult breathing. Babies commonly breathe faster, may have short periods of rapid breathing, and can have brief pauses during sleep. But there is an important line between an unusual-looking breathing pattern and visible effort to breathe.
The key is learning what your baby’s chest, ribs, nose, color, and feeding behavior are telling you.
What You'll Discover:
What Normal Baby Breathing Looks Like
Newborns normally breathe much faster than adults. A typical newborn respiratory rate is around 30 to 60 breaths per minute, although the exact rate varies with age, activity, and whether the baby is calm or crying.
A newborn’s breathing may also be irregular. During sleep, a baby can briefly stop breathing for several seconds and then resume with a few faster breaths. This pattern, called periodic breathing, is generally considered normal when the pauses are brief and the baby remains comfortable and does not change color.
Normal newborn breathing can be irregular; respiratory distress is defined more by increased effort, abnormal color, persistent fast breathing, or difficulty feeding than by an occasional unusual breath.
What you may see when breathing is normal
A healthy, comfortable newborn may have:
- A gently rising and falling belly
- Breathing that speeds up briefly and then settles
- Short pauses lasting a few seconds during sleep
- Occasional sighs, snorts, or other little noises
- A respiratory rate that changes with crying, feeding, or activity
- Normal skin and lip color
- Comfortable feeding without repeatedly stopping to catch a breath
Babies often rely heavily on their diaphragm, the large muscle beneath the lungs, to breathe. Their soft, flexible chest wall also makes their breathing movements more noticeable than an older child’s.
What Are Retractions in a Baby?
Retractions happen when the tissues of the chest or neck visibly pull inward during inhalation. They occur because the baby is generating greater negative pressure to move air into the lungs and is recruiting additional muscles to breathe.
Think of normal breathing as a door opening smoothly on its hinges. With increased work of breathing, it is more like trying to open that same door against resistance, the body has to work harder with every breath.
Retractions can appear in several locations.
Intercostal retractions
These occur between the ribs. You may see the skin sink inward between individual ribs each time the baby inhales.
This is one of the classic signs parents are referring to when they say their baby’s “ribs are sucking in.” Pediatric sources identify rib retractions as a sign of respiratory distress.
Subcostal or substernal retractions
These occur below the rib cage or around the lower breastbone. The skin may pull inward underneath the ribs as the baby breathes in.
This can be particularly noticeable because infants naturally have prominent belly movement. The important distinction is whether the soft tissue is being pulled sharply inward around or underneath the ribs, rather than simply seeing the abdomen rise and fall.
Suprasternal retractions
These occur around the base of the neck or above the breastbone. You may see a small hollow develop above the sternum during inhalation.
Retractions in several locations, particularly when combined with fast breathing, grunting, nasal flaring, or color changes, are more concerning than an isolated unusual-looking breath.
Normal Baby Breathing vs Retractions: The Key Differences
| Sign | More consistent with normal breathing | More concerning for respiratory distress |
| Belly movement | Belly gently rises and falls | May be accompanied by forceful inward pulling below ribs |
| Breathing rate | Variable; brief periods of faster breathing can occur | Persistently much faster than usual |
| Pauses | Brief pauses, particularly during sleep | Prolonged pauses or pauses with color change |
| Ribs | Chest moves without obvious sucking-in | Skin between or below ribs pulls inward with breaths |
| Nose | Usually relaxed | Nostrils repeatedly flare with breaths |
| Sounds | Occasional snorts or mild noises | Persistent grunting, wheezing, or high-pitched breathing |
| Color | Normal for the baby | Blue, gray, pale, or markedly dusky lips/skin |
| Feeding | Able to feed comfortably | Too breathless, tired, or poorly coordinated to feed |
The overall pattern matters. A baby who briefly breathes rapidly after crying but quickly settles and feeds normally is very different from a baby who remains tachypneic while the ribs visibly pull inward with every breath.
How to Tell If the Ribs Are Really Retracting
This is where many parents get stuck.
Try observing the baby when they are calm, rather than crying. Look at the chest and abdomen from the front and side, ideally with the baby comfortably positioned and without blankets covering the torso.
Watch several breaths rather than judging a single breath.
You are looking for repeated inward movement of the skin between the ribs, underneath the rib cage, or above the breastbone as the baby breathes in. If the same inward pulling happens over and over while the baby is resting, it is more concerning than a single unusual movement.
A short video can also be useful to show a pediatric clinician if the breathing changes intermittently, although a video should not delay urgent medical care when the baby is struggling to breathe.
Belly Breathing Is Not Automatically a Retraction
One of the most common sources of confusion is belly breathing.
Young babies naturally use their diaphragm extensively, so their abdomen may visibly rise with each breath. That movement alone is not the same thing as respiratory distress.
The concern is different when the abdomen or area beneath the ribs pulls sharply inward during inhalation, especially if this is accompanied by other signs of increased work of breathing.
In other words: a moving belly can be normal; a baby visibly fighting for each breath is not.
Other Signs That Breathing May Be Difficult
Retractions rarely need to be considered in isolation. Look at the whole baby.
Nasal flaring
Nasal flaring means the nostrils widen noticeably with each breath. It is a sign that the baby may be working harder to move air.
Grunting
A baby may make a short grunting sound, often while breathing out. Persistent expiratory grunting can be a compensatory effort to keep the small airways and air sacs open and is considered a sign of respiratory distress.
Persistent fast breathing
A newborn respiratory rate above 60 breaths per minute is commonly treated as tachypnea and warrants attention, particularly when it persists while the baby is calm.
If you count breaths, count for a full minute, because newborn breathing can be irregular.
Trouble feeding
Feeding is surprisingly useful as a window into respiratory effort. A baby who is too breathless to suck, repeatedly stops to breathe, becomes exhausted during feeds, or suddenly feeds much less needs prompt medical assessment.
Color changes
Blue, gray, or markedly pale lips or skin can signal inadequate oxygenation or another serious problem. Central blue discoloration is not considered a normal breathing variation.
When Retractions Need Urgent Medical Attention
A baby who is visibly working hard to breathe should be assessed promptly. Emergency warning signs include retractions together with persistent rapid breathing, nasal flaring, grunting, significant difficulty feeding, pauses in breathing, or blue/gray coloration.
If the baby is struggling for each breath, turning blue or gray, becoming unusually difficult to wake, having prolonged breathing pauses, or unable to feed because of breathlessness, seek emergency medical care immediately.
For a newborn, it is safer to have significant breathing difficulty evaluated than to assume it is simply normal newborn breathing.
Why Retractions Can Happen
Retractions are a sign, not a diagnosis. They can occur when a baby’s lungs or airways are having difficulty moving air.
Possible causes include respiratory infections such as bronchiolitis, transient tachypnea of the newborn, respiratory distress syndrome in premature infants, pneumonia, airway obstruction, and other heart or lung conditions.
The baby’s age and circumstances matter enormously. Mild respiratory findings during the first hours after birth can sometimes occur as the lungs transition to life outside the womb, whereas new or worsening retractions later at home deserve medical attention.
A Simple Parent Check: Look, Listen, and Watch
When you’re unsure whether a baby’s breathing is normal, use three observations.
Look
Check whether the ribs, area below the ribs, or base of the neck repeatedly pull inward. Also look for nasal flaring and unusual skin color.
Listen
Listen for persistent grunting, wheezing, stridor, or other new breathing noises. Occasional newborn noises can be harmless, so persistent or effortful sounds are more important than one isolated squeak or snort.
Watch
Look at the baby’s behavior. Can they wake normally? Are they feeding? Do they remain comfortable between breaths? Is the breathing settling, or is the effort continuing or getting worse?
This broader assessment is important because oxygen saturation alone does not perfectly measure respiratory distress. The American Academy of Pediatrics notes that oxygen saturation and work of breathing do not always correlate closely in infants with respiratory illness.
A home pulse oximeter can therefore provide information, but it should not override obvious signs that a baby is struggling to breathe.
Common Misunderstandings About Baby Breathing
“Fast breathing always means something is wrong.”
Not necessarily. Newborns can briefly breathe rapidly, especially during or after activity, and periodic breathing can include short bursts of faster breathing. The concern is persistent fast breathing, especially when other signs of distress appear.
“Belly breathing means my baby is retracting.”
Not by itself. Visible abdominal movement is common in infants because of their reliance on diaphragmatic breathing. Retractions involve abnormal inward pulling of the soft tissues during inhalation.
“If my baby’s oxygen reading is okay, the breathing must be okay.”
Not necessarily. Respiratory distress is assessed clinically using the baby’s breathing effort, respiratory rate, appearance, feeding ability, and other findings, not a single number from a home device.
Frequently Asked Questions
Is it normal for a newborn to breathe fast sometimes?
Yes. Newborns naturally breathe faster than adults, and short periods of rapid breathing can occur normally. Persistent rapid breathing, particularly above 60 breaths per minute when calm, should be assessed in context.
What do baby retractions look like?
Retractions look like the skin being pulled inward around or between the ribs, beneath the rib cage, or above the breastbone during inhalation. They indicate increased work of breathing and are more concerning when persistent or accompanied by other distress signs.
Is belly breathing normal in babies?
Often, yes. Infants commonly use their diaphragm, so their belly may rise and fall visibly with each breath. Forceful inward pulling beneath the ribs is different and can indicate respiratory distress.
How long can a newborn normally pause breathing?
Brief pauses of several seconds can occur as part of normal periodic breathing. Pauses lasting longer than about 10 seconds, particularly when associated with color change or other symptoms, require medical attention.
When should I take a baby with breathing problems to emergency care?
Seek emergency care if the baby is struggling for each breath, has significant or worsening retractions, turns blue or gray, has prolonged breathing pauses, makes persistent grunting sounds, or is too breathless to feed.
Key Takeaways
- Normal baby breathing can be fast and irregular, particularly during the newborn period.
- Brief pauses of several seconds can be part of normal periodic breathing when the baby remains comfortable and maintains normal color.
- Retractions are inward pulling of the skin around the ribs, beneath the ribs, or near the breastbone during breathing.
- Belly movement alone is usually not the same as retractions; infants commonly use their diaphragm to breathe.
- Persistent fast breathing, nasal flaring, grunting, unusual color, or difficulty feeding makes breathing problems more concerning.
- A baby who is visibly struggling to breathe needs prompt medical assessment.
- When in doubt, assess the whole picture, look at the chest, listen to the breathing, and watch the baby’s color, alertness, and feeding.
Additional Resources
- RSV breathing warning signs: This AAP resource explains chest retractions and other warning signs that can accompany respiratory infections in babies and children.





